Wednesday, May 10, 2017

Lost and Found

Three steps in the ocean I found you asleep under sand under sea under sky. 
I carefully lifted you, washed you in waves that had polished you smooth long ago. 
Perhaps you erupted from fiery peaks, or tumbled from mountains of snow?
If only I knew more I'd not have to ask, and I don't think that you will reply.
I wondered what undersea creatures you'd seen, if you'd had eyes to see things at all.
I might have known all of these answers but now, they have flown and won't answer my call.


Sunday, May 7, 2017

Things I Learned in Surgery

  1. Make things easier for yourself: Surgery is hard enough already, so making it easier was a common theme on which attendings would mentor residents in the OR. There were 3 common varieties:
    1. Visualization: If you can't see what you're doing, it is much harder to do it well. More generally, what can be observed can be manipulated, and what can be measured can be managed.
    2. Tool Selection: Is there some other tool that would be better suited to what we're trying to do? That's why we have so many surgical tools in the first place - to make each individual step as easy as possible. There may be more than one way to achieve any task, but some will be better than others.
    3. Ergonomics: Having picked a tool, how can we use it most effectively? Raise the table, choke up on the needle, tilt the wrist...there are so many little things that can make a process easier on the surgeon's body and the patient's.
  2. Make things easier for others: This is definitely a next-level skill, but it's well worth the effort within and outside the OR. As we work toward a common goal, what can I do to help my team do their work more effectively and efficiently? If I'm the leader (e.g. the attending surgeon), how can I help my first assistant help me better?
  3. Stop when you're struggling: Maybe some arteries are oozing more than I'd like. Perhaps my projects are taking longer than expected. Or my patient is not recovering as quickly as they should. Stop. Step back. This is necessary to effectively use #1 and #2 above, but beyond that, this skill is the point of entry to learning and improvement.

Tuesday, May 2, 2017

On manual focus and switching lenses

In the first class of one of the first courses I took in college, I learned a mind-shifting lesson. Majors, or "concentrations" as we called them at Brown, are not just sets of knowledge and skills to learn, though those are important. Every major also holds a hidden gift: a lens. A lens with which to see the world in a distinct way. A lens with which to focus the shining sun of our mind on the world's problems.


For example, a few years ago, I thought about the lenses which mathematics and computer science offer. Each of us actually has several lenses, but we usually only spend time with one or two. Many of us spend decades polishing one lens during our career. We might spend years in graduate school trying to get a clear view of some subject, hoping we have the right lens to do so.

"Blind monks examining an elephant," by Hanabusa Itchō
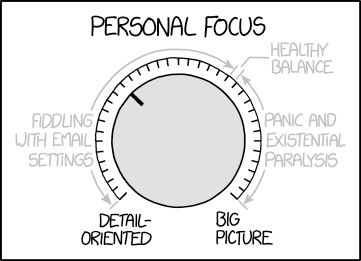
Sometimes Often we argue about problems or facts, because we use different lenses and can't trade. We may also get stuck using our lens at a certain distance, or tunnel in so much that we can't see anything at all. I certainly had the latter experience while on trauma call, as I fixated on the face of a dying man I was helpless to save. In such situations, how do we change focus? How can we zoom out to see the big picture rather than auto-focusing on the nearest, shiniest stimulus? How can we focus mindfully on one subject to avoid getting distracted? How can we switch lenses to see a problem in a whole new way?

xkcd #1796: "Focus Knob"
Part of my medical school training is working out my own answers to these questions, but we have had help. We discover a special lens or two to look inside our own minds at other lenses, to see if they're cracked, or if we're not using them correctly. In our last Learning Communities session, my college discussed ways to tell that it's time to step back. For each step in this metacognitive skill, I think there is room to improve with effort:
  1. Recognizing that it's time to switch: Practice with metacognition; notice tunnel vision or willful ignorance; note when things are not going as I expect.
  2. Zooming out: In my photography, it's become habit to zoom out and refocus when I lose sight of my subject. Likewise, I expect that practicing stepping back when non-urgent but unexpected issues arise will help me do the same in the midst of a critical event.
  3. Building a collection: To pick a new lens, I need a collection to choose from (hopefully in polished condition). The best lesson I've learned here is to look for new lenses everywhere - in books, in people, in classes. To keep them in good repair, it's best to try out a variety as often as I can; this is the more effortful task.
  4. Picking a new lens: This is the hardest part right now. I would like the ability to do this in an automatic System 1 blink as well as the option of running through my top choices systematically. Every lens has certain features they work well on; it'll take some work to identify them.
The Oatmeal: "Believe"
We all have our favorite tools, hammers, lenses, etc. And that's fine. We can't learn and do everything ourselves, and the diversity makes collaboration productive and conversation interesting. Manually focusing deliberately is hard work and hard to learn, and our lightning-fast auto-focus usually gets it right anyway. Yet when reality doesn't match our mental models, when we get tunnel vision, when we fail to understand each other...we should be able to adapt when the world requires it of us.

Sunday, February 19, 2017

A whirlwind friendship


On my walk back from the Children's Hospital today, the sky was blue, the weather warm – a promise of spring after weeks under gloom and chill rain. Birds who had seen me off with happy chirps welcomed me back just as cheerfully, singing out from still-barren trees. As I passed through the parking lot outside my apartment, I heard a crackling reminder of autumn behind me. I turned around and met a young leaf devil, daughter of wind and earth, perhaps two feet high and twice as wide, decked in swirling brown with accents of red and green.

I walked alongside her politely, since we were going the same way, and we gossiped about the capricious clouds and the sweet cool breeze. And then, tired of such trivialities, my new friend swooped toward me, ruffling my hair and throwing leaves past my swinging legs. I found myself in the calm center of a hectic dance that whirled and cackled carelessly. When she moved beside me again, I knew her better; she was an inversion of the inner turbulence we hide behind placid outer masks.

We reached the edge of the lot, and I was surprised by the stately grace with which my friend skipped over the curb and down the sloping grass to the sidewalk, halving her width to slip between the trees in her way. She exchanged some of her leaves for those in the grass and briefly juggled a Styrofoam cup she found, but she soon tossed it back to me when she got bored.

We were now just across the street from my apartment. While I waited for a car to pass, she rushed forward recklessly and barely missed a collision (though I think she did lose a few leaves). Yet she then waited patiently for me to join her again, playing with flowers while I crossed. I thanked her for walking me to my building, and we bid each other goodbye. As I opened the door, I watched my friend drop the rest of her leaves and vanish into the air, joining the sweet cool breeze that tickled my face.

PS - If you have no idea what I'm talking about, check out her cousin here.

Monday, October 5, 2015

LC 9/18/15: Patient Narratives

Every story needs a villain
From a Learning Communities discussion on September 18, 2015
On patient narratives and patient perspective

Communication is complicated. What we mean and what others hear sometimes have as much similarity as two ends of a game of “telephone.” We have different perspectives, emotions, and knowledge. Most of us are novices at the subtleties of non-verbal communication. Words themselves may have different meanings and associations in different brains. “Chronic” to a medical student means long-term, but I have watched it echo around a patient’s mind with a ring of terminal illness and mortality.

One way we deal with all these differences is to provide context and embed our words in narratives. Our brains are stellar at rationalizing cause and effect, at finding patterns, at remembering stories. Therefore, as a physician I should really pay attention to my patients’ narratives, for I will then have the best chance of understanding their illnesses. As William Osler famously said, “Listen to your patient, he is telling you the diagnosis.”

What else can we derive from the narrative’s centrality? Every story needs a villain. Thus patients (and doctors) are often anxious to find it, and can go through even greater anxiety if they are told that the villain is not what they thought it was! Even worse is the occasion when we must tell a patient the diagnosis they have held is false, but we do not yet know the true culprit. As any horror story shows, we fear the unknown evil far more than the known villain. Worse still is when patients hear that they themselves are the problem, even if that is not what we meant to say. This crops up far more often than we would like, when diagnosing psychiatric disorders and suggesting lifestyle changes. Such situations require great care to navigate successfully.

What if the patient thinks the health care system or the doctor is the villain of the story? How can we break that narrative? The most direct, and perhaps best, way is explicit reiteration of my commitment and desire to help them. Even if my patient does not see me as a villain, it is still useful to know what role I play in my patient’s mental story. If I know that I am a confidant, an advisor, or an educator, I can act accordingly, or if necessary try to change it. And what about my story? I think that if we have a chance to truly empathize or connect with a patient, we should snatch the chance to build rapport. Perhaps if I tell some of my stories, my patients will feel more free to share theirs.

Thursday, September 17, 2015

Cognitive Heuristics in Patient Narratives

In preparation for a Learning Communities discussion on September 18, 2015

The peak-end rule: people judge experiences by their peak (i.e. the most intense point) and their end, rather than the sum or average of every moment of the experiences.

Duration neglect: people's judgments of the pleasantness or unpleasantness of experiences depend little on their duration.
 
Barring conscious self-monitoring, the peak-end rule and duration neglect are powerful and often non-intuitive biases governing most people's thoughts about narratives most of the time. This applies to both patients and their families as well as ourselves and our colleagues. How can we use this knowledge of psychology to enhance our practice of medicine? Such a question can be applied when listening to and assessing medical narratives or when communicating with patients and the rest of our team. It can be asked short-term to a single visit or long-term over the course of months and years.

Some applications may be generally intuitive. When comparing a high-pain, short-duration treatment with a low-pain, longer-duration treatment, the latter is typically preferable, all else equal. Likewise, acutely painful conditions evoke more sympathy than chronic diseases with marginal effects on quality of life. When asking a patient for the severity of pain on a 1-10 scale, we understand that the patient's response will lie closer to the peak than to the average and act appropriately. We are much more likely to receive a fuller description of pain severity ("sometimes it hurts a little, but every now and then it's a 5 out of 10") as part of the patient's narrative in response to an open-ended question, rather than a closed-ended 1-10 inquiry.

On an optimistic note, patient memories of doctor appointments are biased by the peak-end rule and duration neglect. This means that even if visit times decline from 45 to 30 to 15 minutes, maintaining the same high level of engagement, compassion, and interest (especially toward the end of the visit) may have an equally therapeutic effect on the patient. Even a few crucial moments of excellent rapport and empathy can dramatically affect perception of an otherwise uneventful or even troubling appointment. However, moments of poor professionalism or severe neglect in the course of a typical visit may conversely affect patient's memories more than one might expect.

Another important area where these rules may come into play is end-of-life and palliative care. What implications do they have for patient and physician decisions in such situations, and how might we address them? Or should we address them at all? At the very least, we must identify them to answer this question.

Sunday, September 13, 2015

Lessons from our VMSI Wellness Retreat

From September 11, 2015
  1. To thrive and not just survive, I must consider what health, balance, and success mean to me and prioritize that. However, the work-life scale is dynamic and is naturally heavier on either side sometimes. I must also remember to re-assess all of this periodically, because those meanings can shift as I change over my life.
  2. Acknowledging the inevitability of imperfection can help me deal proactively with failure. Even better is non-judgmental self-assessment of the causes of that failure, followed by gap analysis and goal-setting to improve in the future.
  3. After I fail in some way, I will feel way worse for longer if I used a shortcut or did not do my best before failing. Note that this is true even if my shortcut or lapse didn’t cause the failure. If I did my best in preparation and execution, then my mind will not be so plagued after failure with regrets and self-doubt.
  4. Recognizing that life has highs and lows (and medicine has high highs and low lows) can reduce the pain of failure and let me have a more temperate temperament. Great achievements and dismal failures will inevitably happen, and they will both pass.
  5. Talking with other people, experiencing their empathy, and hearing their stories of mistakes can alleviate the severity and duration of the crippling pain of failure. If I am lucky (or proactively ask), I might even get ideas about how to avoid such mistakes myself. I don’t have time to experience every failure, so I must experience most vicariously. By extension, I should latch on to people who have experience and know what they’re doing to absorb as many delicious life lessons, tips, and tricks as I can.
  6. I have so many resources for support and advice. (And I probably will wherever I go.) I must not wait to go use these resources if I'm struggling. Honest self-assessment of weakness is itself my greatest strength as a learner and doctor, and so I should act on it quickly and efficiently.